


In 1988, a Rutgers psychologist named Neil Weinstein published a paper that quietly broke one of the most expensive assumptions in public health: that everyone who has not yet acted on a health warning is in the same psychological state. Nearly four decades later, governments running vaccination drives and Fortune 500 marketers running multi-million-dollar campaigns are still making that same mistake, and the brochures, push notifications, and ad creatives they ship to “non-adopters” are still failing for the reasons Weinstein named.
The fix is not bigger budgets or louder copy. The fix is admitting that “hasn’t done it yet” is six different psychological states, that each one needs a different message, and that aiming the wrong message at the wrong stage doesn’t just waste impressions — it can push someone backward.
That insight became the Precaution Adoption Process Model. It’s the most under-rated stage-based behavior-change framework in the field, partly because it sits in the shadow of Prochaska’s better-known Transtheoretical Model, and partly because its most important contribution — Stage 4, “Decided NOT to Act” — is the one most campaigners would rather pretend doesn’t exist.
This pillar takes you through all seven stages, the stage-matched intervention thesis Weinstein built around them, the brain science underneath each transition, the places PAPM falls apart, and the design protocol I run on every behavior-change brief where the audience isn’t a monolith. By the end you’ll have an audit you can run on any campaign you’re shipping next quarter, and a Stage 4 re-engagement playbook you almost certainly don’t have today.

Speed Run Notes
- Most behavior-change campaigns fail because they broadcast one message to an audience that is actually in six different psychological stages. PAPM is the stage map.
- The seven stages: Unaware, Unengaged, Deciding, Decided NOT to Act, Decided to Act, Acting, Maintenance. Stage 4 is an off-ramp, not a pause.
- Stage-matched intervention is the thesis: the variable that moves someone from Stage 2 to Stage 3 is qualitatively different from the variable that moves Stage 5 to Stage 6. Same message, wrong stage, wasted reach.
- PAPM separates “doesn’t know” from “knows but isn’t engaged.” TTM lumps them into Precontemplation, which is why TTM-tailored radon and vaccination campaigns underperform PAPM-tailored ones.
- Octalysis crosswalk: Stage 1-2 runs on Curiosity. Stage 2-3 on personalized Loss + Ownership. Stage 3-5 on Social Influence. Stage 5-6 on Scarcity plus friction-removal. Wrong Drive, wrong stage, no movement.
- The Stage 4 playbook nobody runs: people who decided NOT to act need a different message than the undecided. Treating them as “still deciding” is the most common Stage 4 mistake in field campaigns.
In This Article
- What Is the Precaution Adoption Process Model?
- The Seven PAPM Stages, In Order
- The Stage-Matched Intervention Thesis
- What Weinstein Got Right
- Where PAPM Falls Apart
- What’s Really Happening Inside the Brain
- PAPM vs Other Theories
- PAPM in the Real World
- The Elephant in the Room
- How to Apply PAPM with the Octalysis Framework
- Frequently Asked Questions
Author Credibility: Yu-kai Chou

Yu-kai Chou created the Octalysis Framework after studying gamification since 2003 — years before the term entered mainstream vocabulary. As a Human-Systems Architect & Behavioral Designer, his framework has been applied by LEGO, Microsoft, Porsche, Coca-Cola, Salesforce, and MrBeast, impacting over 1.5 Billion Users.
Chou has taught the Octalysis methodology at Harvard, Stanford, Yale, Tesla, Google, BCG, and IDEO.
His work has been cited by Harvard, Stanford, MIT, Forbes, Wall Street Journal, Wired, US Department of Energy, NIST, NSF, NCBI, US Department of Education, ClinicalTrials.gov, and Google Scholar — with 3,700+ more academic publications. Explore his books here.

What Is the Precaution Adoption Process Model?
The Precaution Adoption Process Model (PAPM) is a seven-stage map of how a person moves from total ignorance about a health risk or behavior to fully integrated, sustained action on it. It was developed by Neil Weinstein and colleagues at Rutgers in the late 1980s and refined across a series of empirical studies through the 1990s, with the canonical extended treatment appearing in Weinstein, Sandman & Blalock’s 2008 chapter in Health Behavior and Health Education.
The core claim is structural, not motivational. PAPM does not tell you what makes someone want to do something. It tells you what stage they’re in right now, what the next stage looks like, and what kind of input will actually move them. The model assumes that the psychological barrier between any two adjacent stages is qualitatively different from the barrier between any other two stages, which means that the intervention that worked at one transition can backfire at another.
That single assumption is the whole reason the model exists. Most behavior-change campaigns, from public-health vaccination drives to SaaS onboarding emails, treat the people they’re trying to convert as one homogenous “non-adopter” segment and broadcast one persuasion message. PAPM says that approach is hitting Stage 1 readers with Stage 5 cues, Stage 4 readers with Stage 3 cues, and Stage 6 readers with Stage 7 cues — and the conversion data should look exactly like that mismatch predicts.
The original empirical anchor was radon. In the late 1980s the United States Environmental Protection Agency (EPA) was running a national radon-testing campaign that was, on paper, well-funded and competently designed. It was also failing. Weinstein and his colleague Peter Sandman ran a series of studies on New Jersey homeowners and found something the EPA’s planners had missed: the homeowners who hadn’t tested their homes weren’t all “not yet convinced.” Some hadn’t heard of radon at all. Some had heard of it but had never connected it to their own house. Some had thought about testing and concluded it wasn’t worth the trouble. Some were going to test next month. Sending those four groups the same brochure was a recipe for underperformance.
Weinstein and Sandman’s 1992 Health Psychology paper, the one that gave the model its name, pulled those New Jersey surveys and follow-ups together. Its central finding was that, apart from people who said they planned to test, few homeowners went on to order a radon test, so planning to act looked like a qualitative step rather than a slightly stronger version of being undecided. The experimental test of stage-matched messages came six years later in Columbus, Ohio, and it is the result every stage-matched PAPM application has leaned on since (it is covered in the stage-matched thesis section below).
The Seven PAPM Stages, In Order
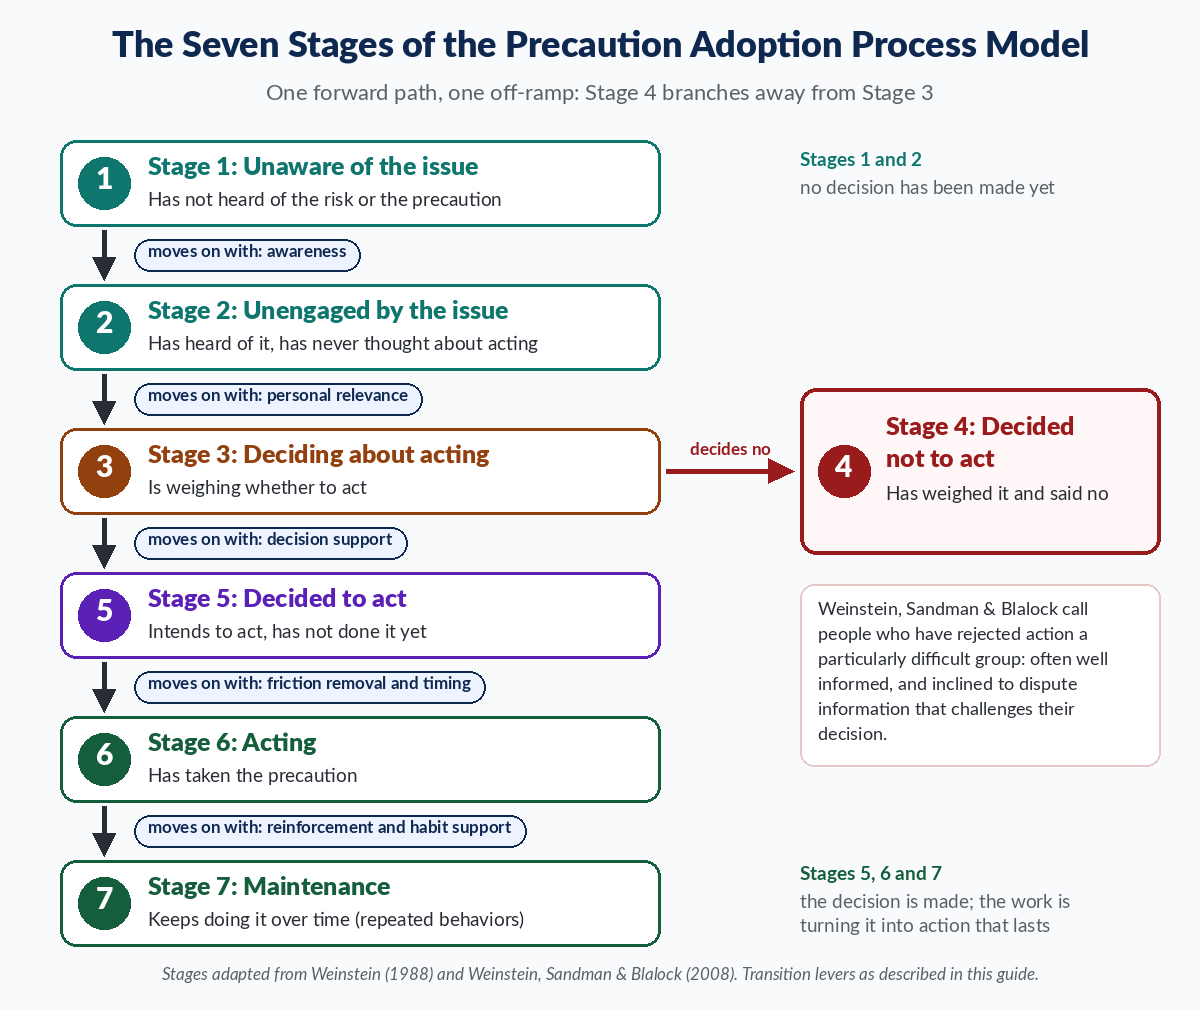
The model’s structure is a directed graph with seven nodes and one side branch. Most accounts present the stages as a linear sequence, but the actual model has an off-ramp at Stage 4 that linear diagrams hide. Reading the stages in order, the underlying psychology of each one looks like this.
Stage 1: Unaware of the Issue
The person has not heard of the risk or the behavior. The marketer’s instinct is to skip past this stage, because surely everyone has heard of X by now. Sometimes the instinct is right, but it has to be measured, not assumed. When Weinstein’s team recruited for their 1998 radon experiment in Columbus, Ohio, only 3.8% of the 24,484 people they interviewed had never heard of radon, because radon had been in the news for years by then. For a new vaccine, a new screening test or a new financial product, the unaware share can be far larger, and it is the share most campaigns forget to measure.
The intervention at this stage is awareness. Not persuasion, not benefits, not call-to-action language. Awareness. The person at Stage 1 cannot evaluate benefits because they don’t yet know the category exists, so any message that assumes prior knowledge (“Have you tested your home for radon yet?”) simply reads as background noise.
Stage 2: Unengaged by the Issue
The person has heard of the issue but has not personally engaged with it. They could define radon if asked, or they could state that their HPV vaccination is overdue, but the issue lives in the abstract — it’s something other people deal with. This is the stage where the EPA’s well-meaning brochures landed in 1989 and where most disease-awareness campaigns still land today. Weinstein, Sandman and Blalock report that in a 1986 radon survey, half of the respondents in a high-risk region said they had never thought about testing their homes, even though all of them knew what radon was.
The intervention at this stage is personalization. The person needs to move the issue from the category of “things that exist” to the category of “things that exist for me.” That move is psychological, not informational. Adding more facts does not work; what works is a personal-risk anchor — a neighbor’s positive test result, a zip-code-specific risk map, a family-history calculator that returns a number with their name attached. The shift from Stage 2 to Stage 3 is the shift from “this is real” to “this is real for me.”
Stage 3: Deciding About Acting
The person is actively weighing the decision. They are engaged. They are doing the cost-benefit math. They are reading reviews, asking friends, looking at their schedule. This is the stage where the Health Belief Model variables (perceived susceptibility, perceived severity, perceived benefits, perceived barriers, cues to action) finally start to do their predictive work. Before Stage 3, those variables are inert because the person isn’t running the calculation yet.
The intervention at this stage is decision-support. The Stage 3 person doesn’t need more awareness or more personalization; they need help with the deliberation. Comparison tables, removed barriers, social proof from peers who have already decided, and a clear sense of what the next action would actually involve. This is also the most fragile stage, because every Stage 3 deliberation has two possible exits — Stage 4 (decided not to act) or Stage 5 (decided to act). Stage 4 is the harder of the two to come back from.
Stage 4: Decided Not to Act
This is the stage every other behavior-change model under-theorizes. The person has weighed the decision and concluded that the precaution is not for them. Maybe they decided the risk isn’t real. Maybe they decided it’s real but not large enough to act on. Maybe they decided the cost is too high. Maybe they ran into a barrier they couldn’t get past, accepted the barrier, and stopped thinking about it.
Critically, the Stage 4 person is not the same as the Stage 2 person. The Stage 2 person hasn’t deliberated yet. The Stage 4 person has, and has finished the deliberation in the “no” direction. The psychological consequence is that the Stage 4 person now has a sunk-cost defense around the decision — they’ve already publicly or privately committed to not acting, and re-opening the decision feels like admitting they were wrong before. Treating a Stage 4 audience the same way you treat a Stage 2 audience is one of the single most common mistakes in vaccination outreach, where “vaccine-hesitant” populations are routinely re-targeted with the same awareness-and-personalization content that already failed once.
The intervention at Stage 4 is qualitatively different from any earlier stage. The Stage 4 person needs a face-saving on-ramp back to deliberation — usually a change in the underlying facts (“the new variant changes the calculation”), a change in their personal circumstances (“now that you’ve had a child”), or a change in the cost-side of the decision (“the test is now free”). Pushing a Stage 4 person without one of these external reframes typically deepens the Stage 4 commitment via reactance.
Stage 5: Decided to Act
The person has formed the intention. They are going to test for radon, schedule the vaccination, sign up for the program. They have not done it yet. The gap between Stage 5 and Stage 6 is the famous intention-behavior gap, and Sheeran’s 2002 review of health-behavior studies found that a median of 47% of people with positive intentions did not perform the behavior — only about half of people who form a clear behavioral intention actually carry it out, even when they sincerely mean to.
The intervention at this stage is friction-reduction and timing. The person doesn’t need more persuasion; the persuasion already worked. They need the action to be easy, scheduled, and unavoidable. Implementation intentions (Gollwitzer’s “if-then” planning), default scheduling, default appointment booking, calendar invites, “do this within 24 hours and we’ll waive the fee” deadlines — these are the Stage 5 levers. Persuasion content here is wasted; it converts a Stage 5 person back into a Stage 3 person by inviting them to re-deliberate a decision they’ve already made.
Stage 6: Acting
The person has performed the behavior. This is the stage everyone celebrates as if it’s the finish line, and for one-time precautions (radon test, single-shot vaccination) it largely is. But for any behavior that requires repetition (annual mammograms, daily medication, recurring screenings, ongoing dietary change), Stage 6 is the temporary state in which the behavior has been done once and is at risk of not being done again.
The intervention at this stage is reinforcement and habit-scaffolding. The person needs evidence that the behavior worked, social acknowledgment that they’re now in the in-group of doers, and structural supports that make the second performance easier than the first. This is also the stage where the original PAPM model is least specified, because Weinstein’s primary cases were one-time precautions where Stage 6 was effectively terminal. For repeated behaviors, the model needs supplementation from the habit literature.
Stage 7: Maintenance
The behavior has been integrated into the person’s life. They have done it enough times that the cognitive effort of deciding to do it has dropped to near zero. The behavior is now a habit, and the relevant brain machinery has shifted from the deliberative prefrontal-cortex circuits to the dorsolateral striatum’s habit network (Graybiel 2008; Wood & Neal 2007).
The intervention at this stage is protection of the existing habit. The Stage 7 person doesn’t need persuasion or scheduling; they need their existing routine not to be disrupted. The classic Stage 7 mistake is sending the same “have you tested for radon yet?” reminder to someone who has tested twice already, which signals that the campaign doesn’t know who its own users are and produces a Core Drive 8 (CD8): Loss & Avoidance reaction — the person becomes more likely to disengage from future communications.
PAPM Stages at a Glance
The seven PAPM stages side by side, with what a person at each stage is thinking, what moves them on, and the Octalysis lever this guide pairs with each one:
| Stage | Name | What the person is thinking | What moves them on | Octalysis lever |
|---|---|---|---|---|
| Stage 1 | Unaware of the issue | “I’ve never heard of it.” | Awareness | Core Drive 7 (curiosity), then Core Drive 1 |
| Stage 2 | Unengaged by the issue | “I know about it, but I’ve never thought about doing anything.” | Personal relevance | Core Drive 8 (personal loss) with Core Drive 4 |
| Stage 3 | Deciding about acting | “I’m weighing it up.” | Decision support and fewer barriers | Core Drive 5 with Core Drive 2 |
| Stage 4 | Decided not to act | “I’ve thought about it, and it’s not for me.” | A face-saving reason to reopen: new facts, changed circumstances, lower cost | Lower the pressure; change the facts or the cost |
| Stage 5 | Decided to act | “I’m going to do it.” | Friction removal and timing | Core Drive 6 plus one fewer step |
| Stage 6 | Acting | “I’ve done it.” | Reinforcement and habit support | Core Drive 4 (identity) with Core Drive 1 |
| Stage 7 | Maintenance | “It’s just something I do.” | Protecting the routine, not re-persuading | Core Drive 4 (identity) |
The Stage-Matched Intervention Thesis
If the seven stages are the model’s anatomy, the stage-matched intervention thesis is its physiology. Weinstein’s claim is that the relationship between intervention content and stage transition is not linear or additive. A given intervention is uniquely effective at one specific transition and approximately useless — or counterproductive — at all the others.
The cleanest test of this came in Weinstein, Lyon, Sandman & Cuite’s 1998 paper in Health Psychology, a field experiment on home radon testing in Columbus, Ohio. After a short educational video, 1,897 homeowners who had not yet tested were classified as either undecided about testing (Stage 3) or decided to test (Stage 5). They were then randomly assigned to a control condition, a risk message about radon levels in local homes, a low-effort message that showed how to test and came with a test-kit order form, or both. The risk message did more to move undecided people toward deciding to test than it did for people who already planned to. The low-effort message did its work on the planners: 32.5% of them ordered a test, against 8.0% in the control group. The interaction was not subtle.
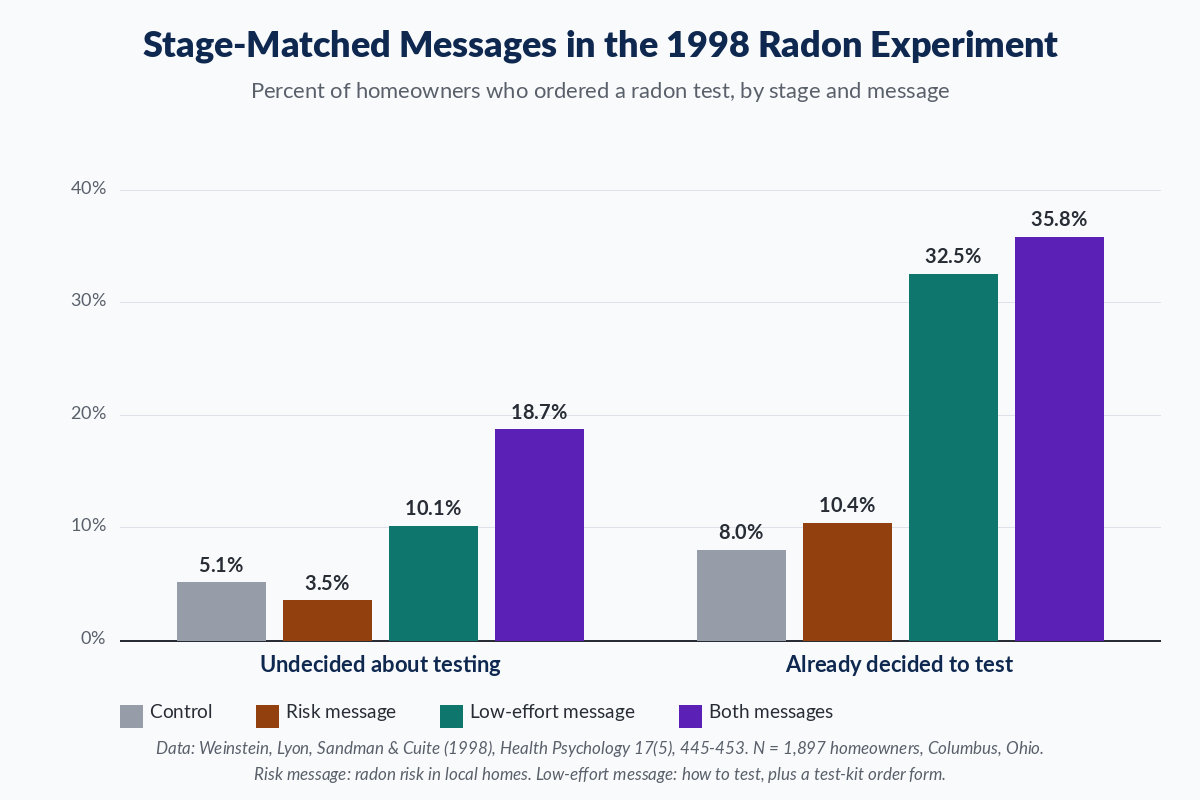
This is the result that grounds the entire PAPM apparatus. Without stage-matched advantage, the seven stages would be a useful taxonomy but not a usable model. With stage-matched advantage, every behavior-change campaign has a hard ceiling determined by how accurately it can identify which stage its audience is in, and how cleanly it can route stage-specific messages to stage-specific recipients.
The implication for practitioners is that the right question is not “is our message persuasive?” The right question is “what stage is each segment of our audience in, and is the message they’re receiving the one that moves their stage?” That question almost no campaign answers, which is why almost no campaign captures the full ceiling.
What Weinstein Got Right
The first thing PAPM gets right that competing models do not is the cleavage between unaware and unengaged. The Transtheoretical Model (TTM), which is older, more cited, and dominant in the smoking-cessation and exercise literatures, lumps Weinstein’s Stage 1 and Stage 2 into a single “Precontemplation” stage. That collapse is harmless if your audience already knows the issue exists, which is roughly true for smoking and exercise in the populations TTM was built for. It is catastrophic if your audience contains a meaningful share of people who haven’t heard of the issue at all, which is true for nearly every novel-precaution campaign ever run — new vaccines, new screenings, new climate-mitigation behaviors, new financial products, new platforms.
The second thing PAPM gets right is Stage 4. Every other major behavior-change model treats “not yet acting” as a single state that can be moved through persuasion. PAPM is the only model that takes seriously the possibility that some non-actors have decided, deliberately and stably, that the precaution is not for them, and that this decision changes the psychological substrate the next intervention has to work with. The Stage 4 distinction is the basis for the “vaccine-hesitant rather than vaccine-uninformed” reframe that came to dominate post-2021 immunization research, and it’s the basis for almost every successful Stage 4 reactivation case study in the field.
The third thing PAPM gets right is the qualitative-rather-than-continuous nature of stage transitions. The Health Belief Model treats perceived susceptibility, severity, benefits, and barriers as continuous variables that combine additively to predict behavior. PAPM doesn’t deny that those variables matter, but it claims they don’t matter equally at every stage. Susceptibility moves Stage 2 to Stage 3. It does almost nothing at Stage 5 to Stage 6, where the relevant variable is friction. The shift from continuous-variable models to stage-conditional-variable models is the single most important advance in the precaution literature, and PAPM was the model that made it cleanly.
Where PAPM Falls Apart
PAPM is also wrong in interesting and specific ways. A pillar that doesn’t say so is a brochure, not a guide.
1. It Was Built for Single-Decision Precautions, Not Cycling Behaviors
Weinstein’s original cases — radon testing, mammography, osteoporosis prevention, hepatitis B vaccination — are all behaviors where one decision largely determines the outcome. You test once, get vaccinated once, or start a single screening regimen. The model handles those behaviors crisply. But many of the behaviors public-health practitioners actually need to change are oscillating: smoking, dieting, exercise, alcohol consumption. Those behaviors don’t have a clean “decided to act / now acting” line because the person decides, acts, lapses, decides again, acts, lapses, and so on across years.
The Transtheoretical Model handles this loop more naturally by including an explicit relapse mechanism that returns the person to an earlier stage. PAPM has no explicit relapse loop, which means it can’t natively represent the smoker who decided not to quit in 2015, decided to quit in 2019, quit for a year, and started again in 2022. The honest answer is that PAPM is the better model for one-shot precautions and TTM is the better model for cycling behaviors, and a campaign that needs to handle both should not commit to either model alone.
2. Stage Assessment Is Harder Than the Model Pretends
To stage-match an intervention, you have to know what stage each person is in. The PAPM literature includes a standard stage-classification algorithm that uses self-report items, and the reliability of that algorithm is fine at the extremes (Stage 1 versus Stage 7 is easy) and weak at the middles. The hardest distinction is Stage 2 versus Stage 3, both of which can be self-described as “thinking about it,” and the second-hardest is Stage 3 versus Stage 5, since people in active deliberation often describe themselves as “going to” do something they haven’t yet committed to.
This isn’t just a measurement nuisance. Every misclassified person receives a message built for a different stage, so a noisy classifier eats directly into the stage-matched advantage. Lippke and colleagues’ 2009 test of stage assessments for physical activity and diet reported sensitivities of 70–80%, which they counted as good, and which still leaves one person in five or more in the wrong bucket. Sniehotta and colleagues (2005) tested PAPM’s stage boundaries directly, during a livestock epidemic, by checking whether beliefs about meat consumption jump between stages rather than rising smoothly. The lesson from this work is that the model’s predictions are sharper than its instruments. If you’re building a stage-targeted intervention, your first design decision is the classifier, not the message.
3. The Meta-Analytic Evidence Is Modest, Not Decisive
The Weinstein-Lyon-Sandman-Cuite 1998 radon study is one of the cleanest demonstrations of stage-matched advantage in the literature, but it’s also one of a small number. Lippke and colleagues’ 2010 randomized trial of a stage-matched physical-activity intervention (226 participants) moved significantly more people forward to action than a control condition; Bridle and colleagues’ 2005 systematic review of interventions based on the Transtheoretical Model, which makes analogous claims, found limited evidence for stage-based interventions. The honest summary is that stage-matched interventions reliably outperform single-message broadcasts when the classifier is good and the stage differences are large, and they do not reliably outperform when the classifier is noisy or the stages are close together.
Weinstein and his co-authors, in the 2008 book chapter, are careful to present PAPM as a framework for identifying the barriers between stages rather than a finished intervention theory. The seven stages are well-supported as a typology of where people are. The claim that you can move them by stage-matched messages is well-supported in controlled conditions and only partially supported in messy field conditions.
What’s Really Happening Inside the Brain
The seven stages map cleanly onto a handful of well-characterized neural circuits, and the map makes the model harder to dismiss as a tidy psychological just-so story.
The Stage 1 to Stage 2 transition is, neurally, a novelty-detection event. The brain’s ventral attention network (centered on the temporo-parietal junction and the ventral frontal cortex) tags the new information as worth orienting toward, and the locus coeruleus’s noradrenergic burst marks the moment of “wait, what’s that?” Without that orienting response, the information slides past in a habituated background state and the person stays at Stage 1.
The Stage 2 to Stage 3 transition is a salience-and-self-relevance event. The amygdala flags the issue as personally threatening, and the medial prefrontal cortex re-encodes the issue from “exists” to “applies to me.” The brain machinery is the same machinery the self-referential processing literature has documented for autobiographical memory: when a stimulus is encoded as self-relevant, the medial prefrontal cortex shows reliably stronger activation, and the encoding is deeper and more durable. Stage 2 generic messages don’t engage that circuit because they don’t trigger the self-relevance encoding. Stage 3 personalized messages do.
The Stage 3 deliberation runs through the ventromedial prefrontal cortex and the orbitofrontal cortex, which together do the value-integration math that turns “X has this benefit, Y has this cost” into a single comparable utility. The same circuits handle every other cost-benefit decision the person makes — whether to buy a car, take a job, accept a date. The Stage 3 to Stage 5 transition fires when the integrated value crosses a threshold. The Stage 3 to Stage 4 branch fires when the integrated value lands clearly below it and the person commits to the negative decision.
The Stage 5 to Stage 6 transition is the most-studied neural event in the precaution literature, because the intention-behavior gap is itself a research field. The relevant circuits are the dorsolateral prefrontal cortex (which sustains the intention across delay) and the basal ganglia’s action-initiation network (which converts the intention into an actual motor plan at the moment the behavior is performed). Sheeran & Webb’s 2016 review of the intention-behavior gap catalogs the failure modes: forgotten intentions, missed opportunities to act, competing goals, and old habits that pull the person back toward the non-action default.
The Stage 6 to Stage 7 transition is the classic habit-formation arc, and the relevant literature is Graybiel’s work on the dorsolateral striatum and the chunking of action sequences. As the behavior is repeated, the cognitive control required to perform it drops from prefrontal to striatal, the metabolic cost of performance decreases, and the behavior becomes resistant to disruption. This is why Stage 7 maintenance interventions need to protect the routine, not motivate the actor — the actor is barely involved anymore.
PAPM vs Other Theories
PAPM vs the Transtheoretical Model (Prochaska & DiClemente)
TTM has five stages (Precontemplation, Contemplation, Preparation, Action, Maintenance) plus an explicit relapse mechanism that returns the person to an earlier stage. PAPM has seven stages and no relapse loop. The two models cover overlapping territory but were optimized for different problems. TTM was built on smoking cessation, where the relapse loop is the dominant feature of the data. PAPM was built on radon testing, where relapse is almost never the operative concern.
The cleanest contrast is at the front end. TTM’s Precontemplation is one stage; PAPM’s Stages 1, 2, and 4 are three. If you’re working on a behavior where the bulk of your audience already knows the issue but has heterogeneous reasons for not acting, PAPM is the better-resolved map. If you’re working on a behavior where the bulk of your audience is in some kind of cycling lapse pattern, TTM is the better fit. The post-2010 consensus in the stage-theory literature is that the two models should not be treated as rivals but as differently-tuned instruments — Glanz, Rimer & Viswanath’s Health Behavior and Health Education textbook presents both as canonical and notes the complementarity explicitly.
PAPM vs the Health Belief Model (Rosenstock)
The Health Belief Model is older (1950s origin), simpler, and not staged. It treats four perceived variables — susceptibility, severity, benefits, barriers — plus cues to action as continuous predictors of behavior. PAPM doesn’t replace those variables. It puts them inside a stage architecture and claims they’re operative at different stages: susceptibility and severity dominate the Stage 2→3 transition, benefits and barriers dominate the Stage 3→5 transition, cues to action dominate the Stage 5→6 transition, and none of the original HBM variables really speak to Stage 7 maintenance at all.
The practical implication is that HBM-only campaigns over-index on susceptibility and severity messages, which are powerful in the right stage and noise in the wrong stage. A PAPM-overlay on an HBM campaign tells you when to use which HBM lever and when not to. We covered HBM in depth in the Health Belief Model pillar; this one extends that material rather than replacing it.
PAPM vs the Health Action Process Approach (Schwarzer)
HAPA, developed by Ralf Schwarzer in the 1990s, is the closest direct competitor to PAPM in the stage-theory literature. HAPA compresses PAPM’s seven stages into two broad phases — a motivational phase (deciding to act) and a volitional phase (planning and acting on the intention) — and adds continuous variables for outcome expectancies, self-efficacy, action planning, and coping planning. The HAPA literature argues that the binary motivational/volitional split is the empirically supported stage boundary and that PAPM’s seven-stage carving is more granular than the data justifies.
The HAPA-PAPM debate is not fully resolved, but the position that most stage-theorists have converged on is that HAPA’s binary phases describe the largest, cleanest empirical boundary, while PAPM’s seven-stage granularity is more useful for prescribing specific interventions. In practice, our HAPA pillar and this PAPM pillar are sister maps of the same territory at different resolutions, and a careful campaign uses HAPA’s binary phases for high-level targeting and PAPM’s seven stages for message design.
PAPM vs the Theory of Planned Behavior (Ajzen)
Ajzen’s Theory of Planned Behavior predicts behavioral intention as a function of attitudes, subjective norms, and perceived behavioral control, and then treats intention as the proximate predictor of behavior. TPB does extremely well at predicting where someone is at the Stage 5 line and almost nothing else — it is silent on Stage 1, Stage 2, and Stage 4, and it doesn’t engage the intention-behavior gap that dominates Stage 5 to Stage 6. PAPM’s relationship to TPB is that PAPM tracks the journey before and after the formation of intention, while TPB owns the moment of intention formation itself. The two are complements, not rivals.
PAPM in the Real World
Vaccination Programs
The 2021 to 2023 vaccination push was the largest real-world run of PAPM-style thinking ever attempted, even where the campaigns never cited the model. By mid-2021, “vaccine-hesitant” had become a working category in public-health planning, kept separate from the uninformed — the same line PAPM draws between Stage 4 and Stage 1. Mapped onto the seven stages, the stage-matched playbook looks like this. Stage 1 audiences (those unaware of new variants or new boosters) need pure-information messaging. Stage 2 audiences need geographically and demographically personalized risk content. Stage 3 audiences need decision-support content with peer-comparison data. Stage 4 audiences — the genuinely hesitant rather than the uninformed — need messages keyed to changed circumstances, ideally from trusted community messengers rather than centralized media. Stage 5 audiences need friction-reduction content, including default appointment booking and on-site clinic availability. Stage 6 and Stage 7 audiences need annual-reminder protection, not persuasion.
The lesson is that “the message” is the wrong unit of analysis. The right unit is the stage-message pair. Brewer and colleagues’ 2017 review of vaccination research in Psychological Science in the Public Interest points the same way: the interventions with the strongest record shape behavior directly by building on people who already intend to vaccinate, with reminders, default appointments and easier access, while campaigns aimed at changing what people think and feel showed little evidence of working. In PAPM terms, the Stage 5 levers beat the Stage 2 and Stage 3 levers.
Disaster Preparedness
Hurricane preparedness is a natural PAPM application area, and the research shows why stage-blind warnings struggle. Bostrom and colleagues (2018) combined 28 in-depth mental-models interviews with a survey of 460 residents of three Florida counties and found gaps between how the public and warning professionals perceive hurricane risk, especially the risk of storm-surge flooding. In PAPM terms, a resident who underestimates storm surge can sit at Stage 2 for the threat that matters most while sitting at Stage 5 or 6 for wind.
A stage-matched warning system would send initial-warning content to the unaware, personalized surge-risk content to the unengaged, decision-support content (specific destinations, specific routes, specific check-in points) to those deciding, and friction-removal content (shuttles, shelter and lodging arrangements) to those who have decided to evacuate but haven’t yet left.
Software-as-a-Service Conversion Funnels
Outside health, the cleanest applied use of PAPM is in SaaS conversion analytics. The standard SaaS funnel (Awareness, Consideration, Trial, Purchase, Activation, Retention) is a relabeled PAPM staircase, and the SaaS practitioners who realize this and route stage-specific messages outperform the practitioners who broadcast one onboarding email to every signup. Activation campaigns that branch on what a user has and hasn’t done yet are PAPM at its most legible, even when the product teams have never read Weinstein.
Climate-Action Interventions
The climate-behavior literature has been late to adopt stage-targeting, in part because the climate-action audience has been treated as a single mass for the first three decades of the movement. The newer work, especially the climate-communication studies coming out of Yale’s Program on Climate Change Communication and George Mason’s Center for Climate Change Communication, segments the public into “Global Warming’s Six Americas,” from the Alarmed to the Dismissive. Those segments are not PAPM stages, but they behave like them: the Disengaged look like a Stage 2 audience, and the Dismissive look like a Stage 4 audience that has already decided. The lesson is the same lesson the radon experiment taught in 1998: stage-matched interventions are not optional ornaments. They are the active ingredient.
The Elephant in the Room
The seven stages don’t care whether the behavior you’re moving someone toward is good for them. Stage-matched intervention is a technology, and the same technology that doubled radon-test uptake in 1992 can be used to double credit-card sign-ups, raise smoking initiation rates among teenagers, or move a Stage 4 climate skeptic deeper into the Stage 4 position by exploiting the reactance pattern instead of avoiding it.
This is the unspoken tension at the center of the PAPM literature, and Weinstein himself addressed it only obliquely. The model was published into a public-health environment where the implicit assumption was that the precaution in question was unambiguously the right one. Radon kills people. Vaccines save lives. The implicit ethical framework was that any technology that increased uptake of those behaviors was therefore ethical.
That assumption doesn’t survive contact with private-sector deployment. The same model that segments hesitant vaccine adopters into Stage 4 versus Stage 2 can segment hesitant car buyers, hesitant cryptocurrency purchasers, or hesitant gun owners. The Stage 4 face-saving on-ramp that works for vaccination (“the new variant changes the calculation”) works for crypto (“the new regulations change the calculation”). The model is morally neutral; the only thing that’s not neutral is the campaign’s choice of what behavior to push.
The honest design protocol is to apply the publicity test that Thaler & Sunstein articulated for libertarian paternalism (we covered this in the Libertarian Paternalism pillar). If your stage-segmentation strategy is one you’d be willing to publish in a press release, fully named and stage-keyed, then ship it. If it’s the kind of strategy that would generate a backlash if a journalist explained the back-stage to your target audience, you are running Black Hat Octalysis at a level you should not be running.
The behavioral-design community talks about Black Hat and White Hat Core Drives as if the only ethical concern is the Drive being used. The PAPM literature reveals a second concern: the stage being targeted matters too. Pushing a Stage 4 audience aggressively is a more invasive act than pushing a Stage 3 audience, because the Stage 4 audience has already done the deliberation and you are now overriding their conclusion. A campaign that segments by stage and treats the stages with equal force is using more pressure on its Stage 4 audience than the audience consented to, even if the underlying Core Drive looks White Hat.


How to Apply PAPM with the Octalysis Framework
The Octalysis Framework diagram at the top of this guide arranges the eight Core Drives around the octagon, each Drive paired with the game techniques that activate it. It is the master reference for everything that follows.
The unique contribution this pillar makes is a per-stage Octalysis prescription. Stage-matched intervention is the model’s central thesis, but the model itself doesn’t say which lever to pull at each stage. Octalysis does. The stage-to-Core-Drive map below lines up Weinstein’s seven stages with the eight Drives that move them.
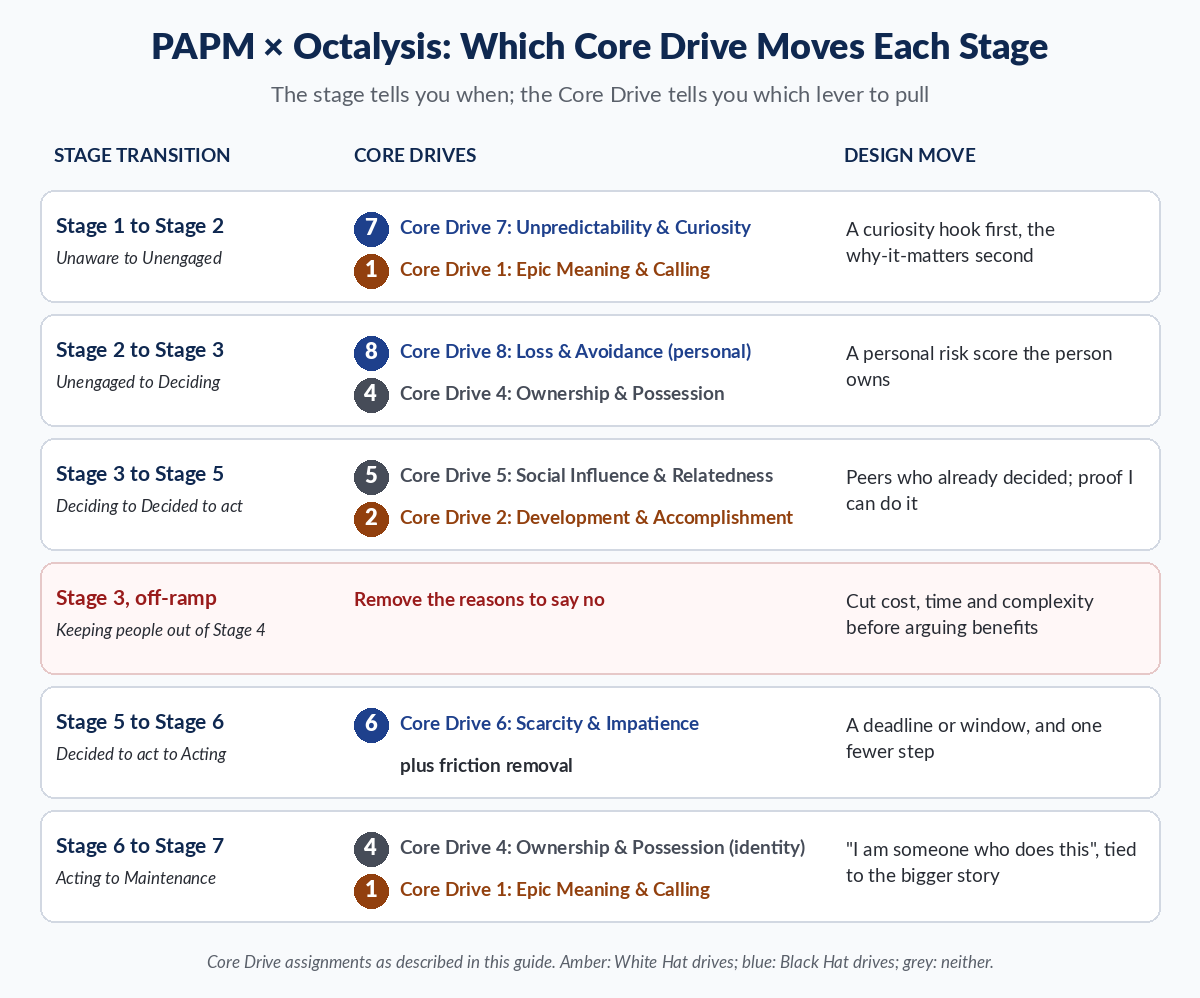
Stage 1 → Stage 2 (Unaware → Unengaged): Core Drive 7 + Core Drive 1
The dominant Drive at the front end of the funnel is Core Drive 7 (CD7): Unpredictability & Curiosity. The Stage 1 audience hasn’t heard of the issue yet, which means the information has to function as a curiosity hook before it functions as anything else. Headlines that promise an answer to a question the reader didn’t know they had outperform headlines that announce facts they already think they know. Secondary Drive: Core Drive 1 (CD1): Epic Meaning & Calling, which provides the why-this-matters context once the curiosity hook has caught attention. The mistake at Stage 1 is to lead with CD1 (epic-meaning-first messaging) before CD7 has done its work; readers don’t engage with epic meaning when the underlying issue is still pre-attentive.
Stage 2 → Stage 3 (Unengaged → Deciding): Core Drive 8 + Core Drive 4
The dominant Drive here is Core Drive 8 (CD8): Loss & Avoidance, but only in its personalized form. Generic loss framing (“radon causes lung cancer”) doesn’t move Stage 2 readers; what moves them is loss attached to their identity (“homes in your zip code show elevated radon levels”). The personalization mechanic is Core Drive 4 (CD4): Ownership & Possession — the person needs to feel that the risk is theirs, not a generic public-health problem. Risk calculators, zip-code maps, family-history tools, neighbor case studies. The intervention endows the person with a personalized risk score they then own and can’t easily disown.
Stage 3 → Stage 5 (Deciding → Decided to Act): Core Drive 5 + Core Drive 2
The dominant Drive at the deliberation stage is Core Drive 5 (CD5): Social Influence & Relatedness, in its peer-comparison form. The Stage 3 deliberator is doing cost-benefit math under uncertainty, and the highest-impact uncertainty-reducer is evidence that their reference group has already decided. Secondary Drive: Core Drive 2 (CD2): Development & Accomplishment, which manages the self-efficacy question (“can I actually do this?”). Testimonials from people the reader sees as similar, completion-rate dashboards, peer-pressure-without-shame norm cues. The mistake at Stage 3 is to lean on CD8 instead of CD5; CD8 worked at the Stage 2 to Stage 3 transition and is now mostly noise.
Stage 3 → Stage 4 Off-Ramp Prevention
The Stage 4 off-ramp is the highest-risk transition in the model, because it is so hard to reverse. The prevention play is to remove the reasons a Stage 3 deliberator would conclude “no.” Most often that means reducing perceived barriers (cost, time, complexity) before reducing perceived benefits. This is also where sludge-removal (covered in the Sludge pillar) does its highest-yield work — friction at Stage 3 doesn’t just slow conversion, it actively converts undecideds into decided-not-to-act through the path-of-least-resistance reflex.
Stage 5 → Stage 6 (Decided to Act → Acting): Core Drive 6 + reduce friction
The dominant Drive at the intention-behavior gap is Core Drive 6 (CD6): Scarcity & Impatience. The person has decided. They are now in danger of indefinitely delaying. The lever is a deadline, a window, a “do it now” mechanic. Implementation intentions that pre-commit to a specific moment (“right after my dentist appointment Friday”), expiring offers, scheduled appointment defaults. The simultaneous lever is friction-removal: every step removed from the action path is worth more at Stage 5 than at any earlier stage, because every step is now a potential indefinite-delay anchor.
Stage 6 → Stage 7 (Acting → Maintenance): Core Drive 4 + Core Drive 1
The dominant Drive at the maintenance transition is again Core Drive 4 (CD4): Ownership & Possession, but in a different form than at Stage 2. At Stage 2, CD4 endowed the person with a risk score. At Stage 7, CD4 endows them with an identity (“I’m someone who tests for radon”). Reinforcing the identity reinforces the behavior, because behavior consistent with identity is easier to repeat than behavior that requires a fresh decision. Secondary Drive: Core Drive 1 (CD1): Epic Meaning & Calling — reconnecting the now-habitual behavior to the larger story keeps it from drifting into rote and getting dropped.
The 6-Step PAPM × Octalysis Audit
This is the audit I run before signing off on any stage-targeted campaign. It’s the protocol that puts the per-stage Octalysis crosswalk into practice.
- Segment by stage, not by demographic. Before any message design, build a stage classifier. The classifier can be a five-question survey, a behavioral inference from past actions, or a self-segmenter (“Which best describes you right now?”). Without a classifier you don’t have a stage-targeted campaign; you have a guess.
- Estimate the stage distribution. Run the classifier on a sample. Most campaigns are surprised by how heavily their audience is concentrated at one stage (often Stage 2, sometimes Stage 4). The distribution determines where to spend.
- Map each stage to its dominant Core Drive. Use the per-stage table above as the starting point. Adjust for behavior-specific deviations (some behaviors have a CD8 Stage 5 that overrides the default CD6).
- Build one message variant per stage. Not one variant per demographic, one variant per stage. The variants will look surprisingly different from each other, which is the point.
- Route stage-matched messages through stage-classified channels. The route matters as much as the message. Stage 4 audiences don’t trust centralized media; route Stage 4 content through community messengers. Stage 5 audiences need friction-removal channels; route Stage 5 content through one-click-action surfaces.
- Run the publicity test on every variant. Before shipping, ask whether you would be willing to publish the full stage-to-message map on the front page of your newsletter. If a stage-message pair fails that test, redesign it. The campaigns that fail the publicity test are the ones that produce backlash when a journalist eventually documents the back-stage strategy.
Practical Steps: Running PAPM This Week
You don’t need a grant or a research budget to apply PAPM to whatever campaign you’re shipping next. Here is the minimum-viable PAPM rollout.
- Write the 5-question stage classifier. Question 1: “Have you heard of [the issue]?” Question 2: “Do you think [the issue] applies to you personally?” Question 3: “Are you actively considering [the behavior]?” Question 4: “Have you decided whether or not to do [the behavior]?” Question 5: “Have you done [the behavior]?” The branching logic gives you a clean Stage 1 through Stage 7 segmentation in under 90 seconds of respondent time.
- Insert the classifier into one channel. The fastest place is your existing email list. A single-question pop-up on your highest-traffic landing page works equally well. The classifier is the campaign’s most important asset; protect the data.
- Draft five message variants, one per stage (combine Stages 1 and 2, combine Stages 6 and 7 if you must). Each variant should be obviously different in tone, evidence type, and call-to-action. If two variants look almost the same, you’ve under-differentiated.
- Build a Stage 4 reactivation track separately. Most teams build four variants and treat Stage 4 the same as Stage 2 or Stage 3. Don’t. Stage 4 needs its own track, keyed to a face-saving reframe (changed circumstances, new evidence, lowered cost). If you don’t have one, document the gap and don’t run Stage 4 outreach until you do.
- Route based on classifier output. Email sequences, push notifications, in-app messages all branch by stage. If your CRM can’t branch, this is the single most important infrastructure upgrade for your behavior-change work.
- Measure stage progression, not just conversion. Track the percentage of your audience moving from Stage N to Stage N+1, not just the percentage that hit Stage 6 this week. The stage-progression metric reveals which variants are doing work and which are noise.
- Re-classify on a regular cadence. Stages aren’t stable on long horizons. Re-run the classifier quarterly for active behaviors, annually for one-time precautions. People move between stages; your campaign should track the movement.
PAPM Was the Beginning, Not the End
The seven stages are not the last word on behavior change. They are the cleanest stage-typology in the precaution literature, and the stage-matched intervention thesis is the cleanest causal claim about why stage-matching matters. But the field has moved on in three specific directions that any modern behavior-change practitioner should know.
First, Schwarzer’s Health Action Process Approach (HAPA) compressed the seven stages into a binary motivational-volitional split and added continuous variables for outcome expectancy, self-efficacy, action planning, and coping planning. Where PAPM stops at “decided to act,” HAPA goes further into the volitional phase and asks the planning question PAPM under-specifies. We covered HAPA in the HAPA pillar, and the two pillars together cover the stage-theory territory at complementary resolutions.
Second, Susan Michie and colleagues’ Capability-Opportunity-Motivation-Behavior (COM-B) model and Behavior Change Wheel reframed the question from “what stage is the person in?” to “what does the person need in order to act?” COM-B’s diagnostic-first stance is a different methodological commitment from PAPM’s typology-first stance. We covered COM-B in the COM-B pillar; a modern stage-targeted campaign should run a COM-B diagnostic alongside the PAPM stage classifier to figure out whether the stage transition is blocked by capability, opportunity, or motivation.
Third, the experimental-policy literature in the Test-Learn-Adapt protocol from the UK Behavioural Insights Team, has shifted the epistemics from “which model is correct” to “which intervention works in this setting, measured by RCT.” PAPM-derived hypotheses are unusually good fodder for that protocol because they generate sharp predictions about stage-message interactions. A campaign that ran a stage-matched intervention through a Test-Learn-Adapt protocol would produce the strongest evidence the field has ever seen on stage-matched advantage in the wild.
The honest summary is that single-model orthodoxy is dead. PAPM is the right model for the stage-typology question, HAPA is the right model for the binary motivation-volition question, COM-B is the right model for the capability-opportunity-motivation diagnostic, and Test-Learn-Adapt is the right epistemic frame for “did the intervention actually work.” A practitioner who uses all four is doing modern behavior-change work. A practitioner who picks one and ignores the others is doing 1990s behavior-change work.
Frequently Asked Questions
What is the Precaution Adoption Process Model?
The Precaution Adoption Process Model (PAPM) is a seven-stage map of how people move from being unaware of a health risk to fully maintaining the behavior that addresses it. It was developed by Neil Weinstein at Rutgers in the late 1980s, validated through a series of studies on radon testing and other precaution behaviors, and formalized in Weinstein, Sandman & Blalock’s 2008 chapter in Health Behavior and Health Education. The model’s central thesis is that different stages need different interventions, and that aiming the wrong intervention at the wrong stage is the single biggest waste of effort in behavior-change campaigns.
Who developed the Precaution Adoption Process Model?
Neil D. Weinstein, a psychologist at Rutgers University, introduced the precaution adoption process in a 1988 Health Psychology paper. He and Peter M. Sandman set out the model and its New Jersey radon evidence in 1992, tested stage-matched messages experimentally with Lyon and Cuite in 1998, and gave the standard textbook account with Susan J. Blalock in 2008.
How does PAPM differ from the Transtheoretical Model?
PAPM has seven stages; the Transtheoretical Model (TTM, Prochaska & DiClemente) has five. PAPM splits the “not yet acting” group into three distinct stages (Unaware, Unengaged, Decided Not to Act) where TTM lumps them into a single Precontemplation stage. PAPM treats Stage 4 (Decided Not to Act) as its own stable branch; TTM treats non-action as part of a cycling lapse pattern. The simplest decision rule: use PAPM for one-time precautions like radon testing or vaccination; use TTM for cycling behaviors like smoking, dieting, or exercise. The two models are complementary rather than competitive.
What are the seven stages of PAPM?
Stage 1 (Unaware of the issue), Stage 2 (Unengaged by the issue), Stage 3 (Deciding about acting), Stage 4 (Decided not to act — the off-ramp), Stage 5 (Decided to act), Stage 6 (Acting), and Stage 7 (Maintenance). Stage 4 branches off from Stage 3; all other stages form a forward sequence. The qualitative-difference claim is that the psychological barriers between adjacent stages are not interchangeable, so the message that moves Stage 2 to Stage 3 will not move Stage 5 to Stage 6.
Why does Weinstein separate “Unaware” and “Unengaged”?
Because the interventions that work for each are completely different. Stage 1 (Unaware) needs awareness content — the person doesn’t know the issue exists, so any persuasion message that assumes prior knowledge bounces off. Stage 2 (Unengaged) needs personalization content — the person knows about the issue but treats it as someone else’s problem, so the lever is personal-risk anchoring. Lumping the two into one “Precontemplation” stage, as TTM does, forces the campaign to choose between awareness content (which wastes Stage 2 readers) and personalization content (which goes over Stage 1 readers’ heads).
What is Stage 4 and why is it important?
Stage 4 (Decided Not to Act) is the stage where the person has weighed the decision and concluded that the precaution isn’t for them. It’s structurally different from Stage 2 (Unengaged) because the Stage 4 person has already done the deliberation and has a sunk-cost defense around the negative conclusion. The Stage 4 reactivation playbook requires a face-saving on-ramp — usually changed external circumstances, new evidence, or a lowered cost — rather than the awareness or personalization content that works at earlier stages. Treating Stage 4 audiences as if they were Stage 2 is one of the most common and most expensive mistakes in vaccination outreach, climate communication, and product re-engagement.
How do you measure which PAPM stage someone is in?
Through a short self-report classifier. The standard algorithm in Weinstein, Sandman & Blalock’s chapter uses three questions: Have you heard of the precaution (Stage 1 if not)? Have you done it (Stage 6, or Stage 7 for a behavior kept up over time)? And which statement best describes your thinking: never thought about it (Stage 2), undecided (Stage 3), decided not to (Stage 4), or decided to (Stage 5)? The reliability is acceptable at the extremes and weaker at the middle distinctions, particularly Stage 2 versus Stage 3 and Stage 3 versus Stage 5. Improving the classifier is the single highest-leverage investment in any stage-targeted campaign.
Does stage-matched intervention actually outperform single-message campaigns?
In controlled studies with good classifiers, yes — Weinstein, Lyon, Sandman & Cuite’s 1998 radon study and Lippke and colleagues’ 2010 physical-activity trial both supported stage-matched intervention. In field studies with noisy classifiers, the advantage shrinks and sometimes disappears. The honest summary is that stage-matched intervention reliably beats single-message broadcast when stage classification accuracy is high and stage differences are large; it doesn’t reliably beat single-message broadcast when classification is noisy or stages are close together. The implication for practitioners is that the classifier matters as much as the message.
How does PAPM compare to the Health Belief Model?
The Health Belief Model (HBM) treats perceived susceptibility, severity, benefits, and barriers as continuous predictors that combine additively to predict behavior. PAPM doesn’t replace those variables; it places them inside a stage architecture and claims they’re operative at different stages. Susceptibility and severity dominate the Stage 2 to Stage 3 transition. Benefits and barriers dominate Stage 3 to Stage 5. None of the original HBM variables speak strongly to Stage 7 maintenance. A PAPM-overlay on an HBM campaign tells you when to use which HBM lever and when not to.
Can PAPM be applied to non-health behaviors?
Yes, and it routinely is, even when practitioners haven’t read Weinstein. Software-as-a-Service (SaaS) funnels (Awareness, Consideration, Trial, Purchase, Activation, Retention) are a relabeled PAPM staircase. Climate communicators segment audiences in a similar way (Yale’s “Six Americas” segments resemble PAPM stages). The seven-stage logic generalizes to any precaution-style or adoption-style behavior where the audience contains a meaningful share of pre-deliberation and post-deliberation members.
How does the Octalysis Framework integrate with PAPM?
Octalysis tells you which Core Drive to activate; PAPM tells you when each Core Drive is operative. Core Drive 7 (Curiosity) dominates Stage 1 to Stage 2. Core Drive 8 (Loss) in its personalized form, paired with Core Drive 4 (Ownership), dominates Stage 2 to Stage 3. Core Drive 5 (Social Influence) and Core Drive 2 (Accomplishment) dominate Stage 3 to Stage 5. Core Drive 6 (Scarcity) plus friction-removal dominates Stage 5 to Stage 6. Core Drive 4 (Ownership of identity) and Core Drive 1 (Epic Meaning) dominate Stage 6 to Stage 7. Pulling the wrong Drive at the wrong stage is the campaign’s single biggest leak. The 6-Step PAPM × Octalysis Audit in the Apply section above is the protocol that makes the crosswalk actionable.
Updated 27 October 2026. Added diagrams of the seven stages, the 1998 radon experiment and the PAPM × Octalysis crosswalk, a stages-at-a-glance table, and corrected the research history: the 1992 paper set out the model from New Jersey survey data, and the stage-matched experiment was the 1998 Columbus study.
References
- Weinstein, N. D. (1988). The precaution adoption process. Health Psychology, 7(4), 355–386.
- Weinstein, N. D., & Sandman, P. M. (1992). A model of the precaution adoption process: Evidence from home radon testing. Health Psychology, 11(3), 170–180.
- Weinstein, N. D., Lyon, J. E., Sandman, P. M., & Cuite, C. L. (1998). Experimental evidence for stages of health behavior change: The precaution adoption process model applied to home radon testing. Health Psychology, 17(5), 445–453.
- Weinstein, N. D., Sandman, P. M., & Blalock, S. J. (2008). The precaution adoption process model. In K. Glanz, B. K. Rimer, & K. Viswanath (Eds.), Health behavior and health education: Theory, research, and practice (4th ed., pp. 123–147). Jossey-Bass.
- Blalock, S. J., DeVellis, B. M., Giorgino, K. B., DeVellis, R. F., Gold, D. T., Dooley, M. A., Anderson, J. J. B., & Smith, S. L. (1996). Osteoporosis prevention in premenopausal women: Using a stage model approach to examine the predictors of behavior. Health Psychology, 15(2), 84–93.
- Hammer, G. P. (1997). Hepatitis B vaccine acceptance among nursing home workers (Doctoral dissertation). Johns Hopkins University.
- Sniehotta, F. F., Luszczynska, A., Scholz, U., & Lippke, S. (2005). Discontinuity patterns in stages of the precaution adoption process model: Meat consumption during a livestock epidemic. British Journal of Health Psychology, 10(2), 221–235.
- Lippke, S., Ziegelmann, J. P., Schwarzer, R., & Velicer, W. F. (2009). Validity of stage assessment in the adoption and maintenance of physical activity and fruit and vegetable consumption. Health Psychology, 28(2), 183–193.
- Lippke, S., Schwarzer, R., Ziegelmann, J. P., Scholz, U., & Schüz, B. (2010). Testing stage-specific effects of a stage-matched intervention: A randomized controlled trial targeting physical exercise and its predictors. Health Education & Behavior, 37(4), 533–546.
- Schwarzer, R. (2008). Modeling health behavior change: How to predict and modify the adoption and maintenance of health behaviors. Applied Psychology, 57(1), 1–29.
- Sheeran, P. (2002). Intention–behavior relations: A conceptual and empirical review. European Review of Social Psychology, 12(1), 1–36.
- Sheeran, P., & Webb, T. L. (2016). The intention–behavior gap. Social and Personality Psychology Compass, 10(9), 503–518.
- Bridle, C., Riemsma, R. P., Pattenden, J., Sowden, A. J., Mather, L., Watt, I. S., & Walker, A. (2005). Systematic review of the effectiveness of health behavior interventions based on the transtheoretical model. Psychology and Health, 20(3), 283–301.
- Brewer, N. T., Chapman, G. B., Rothman, A. J., Leask, J., & Kempe, A. (2017). Increasing vaccination: Putting psychological science into action. Psychological Science in the Public Interest, 18(3), 149–207.
- Bostrom, A., Morss, R. E., Lazo, J. K., Demuth, J. L., Lazrus, H., & Hudson, R. (2018). Eyeing the storm: How residents of coastal Florida see hurricane forecasts and warnings. International Journal of Disaster Risk Reduction, 30, 105–119.
- Rogers, R. W. (1975). A protection motivation theory of fear appeals and attitude change. The Journal of Psychology, 91(1), 93–114.
- Rosenstock, I. M. (1974). Historical origins of the health belief model. Health Education Monographs, 2(4), 328–335.
- Prochaska, J. O., & DiClemente, C. C. (1983). Stages and processes of self-change of smoking: Toward an integrative model of change. Journal of Consulting and Clinical Psychology, 51(3), 390–395.
- Ajzen, I. (1991). The theory of planned behavior. Organizational Behavior and Human Decision Processes, 50(2), 179–211.
- Wood, W., & Neal, D. T. (2007). A new look at habits and the habit-goal interface. Psychological Review, 114(4), 843–863.
- Graybiel, A. M. (2008). Habits, rituals, and the evaluative brain. Annual Review of Neuroscience, 31, 359–387.
- Chou, Y. (2015). Actionable Gamification: Beyond Points, Badges, and Leaderboards. Octalysis Media.
Related Reading
- Behavioral Framework Library — the full hub of behavioral and psychological frameworks every designer should know.
- Health Action Process Approach (HAPA) Explained — the binary-phase model that compressed PAPM’s seven stages.
- Health Belief Model Explained — the continuous-variable model that PAPM extends.
- COM-B and the Behavior Change Wheel — the diagnostic-first complement to PAPM’s typology-first stance.
- Protection Motivation Theory Explained — the threat-and-coping appraisal model PAPM dovetails with at the Stage 2 to Stage 3 transition.
- Sludge Explained — the friction inventory PAPM Stage 5 to Stage 6 needs to address.
- Libertarian Paternalism Explained — the ethics frame for stage-matched persuasion.